
Scleral contact lenses are often considered the best option for Keratoconus patients because they vault over the irregular, cone‑shaped cornea and rest on the white part of the eye (the sclera), creating a smooth, fluid‑filled optical surface — this corrects the distortion from the misshapen cornea and significantly improves visual clarity. Because they don’t touch the sensitive cornea directly, they tend to be much more comfortable and stable than regular rigid or soft contact lenses, even with advanced keratoconus or corneal scarring.

What is Keratoconus
Keratoconus is an eye disease in which the normally round, dome-shaped front surface of the eye — the cornea — thins out and gradually bulges forward, becoming cone-shaped instead of curved like a dome. Because the cornea is responsible for bending (refracting) most of the light that enters the eye, this abnormal cone shape distorts how light is focused — causing vision problems that are different from simple nearsightedness or astigmatism.
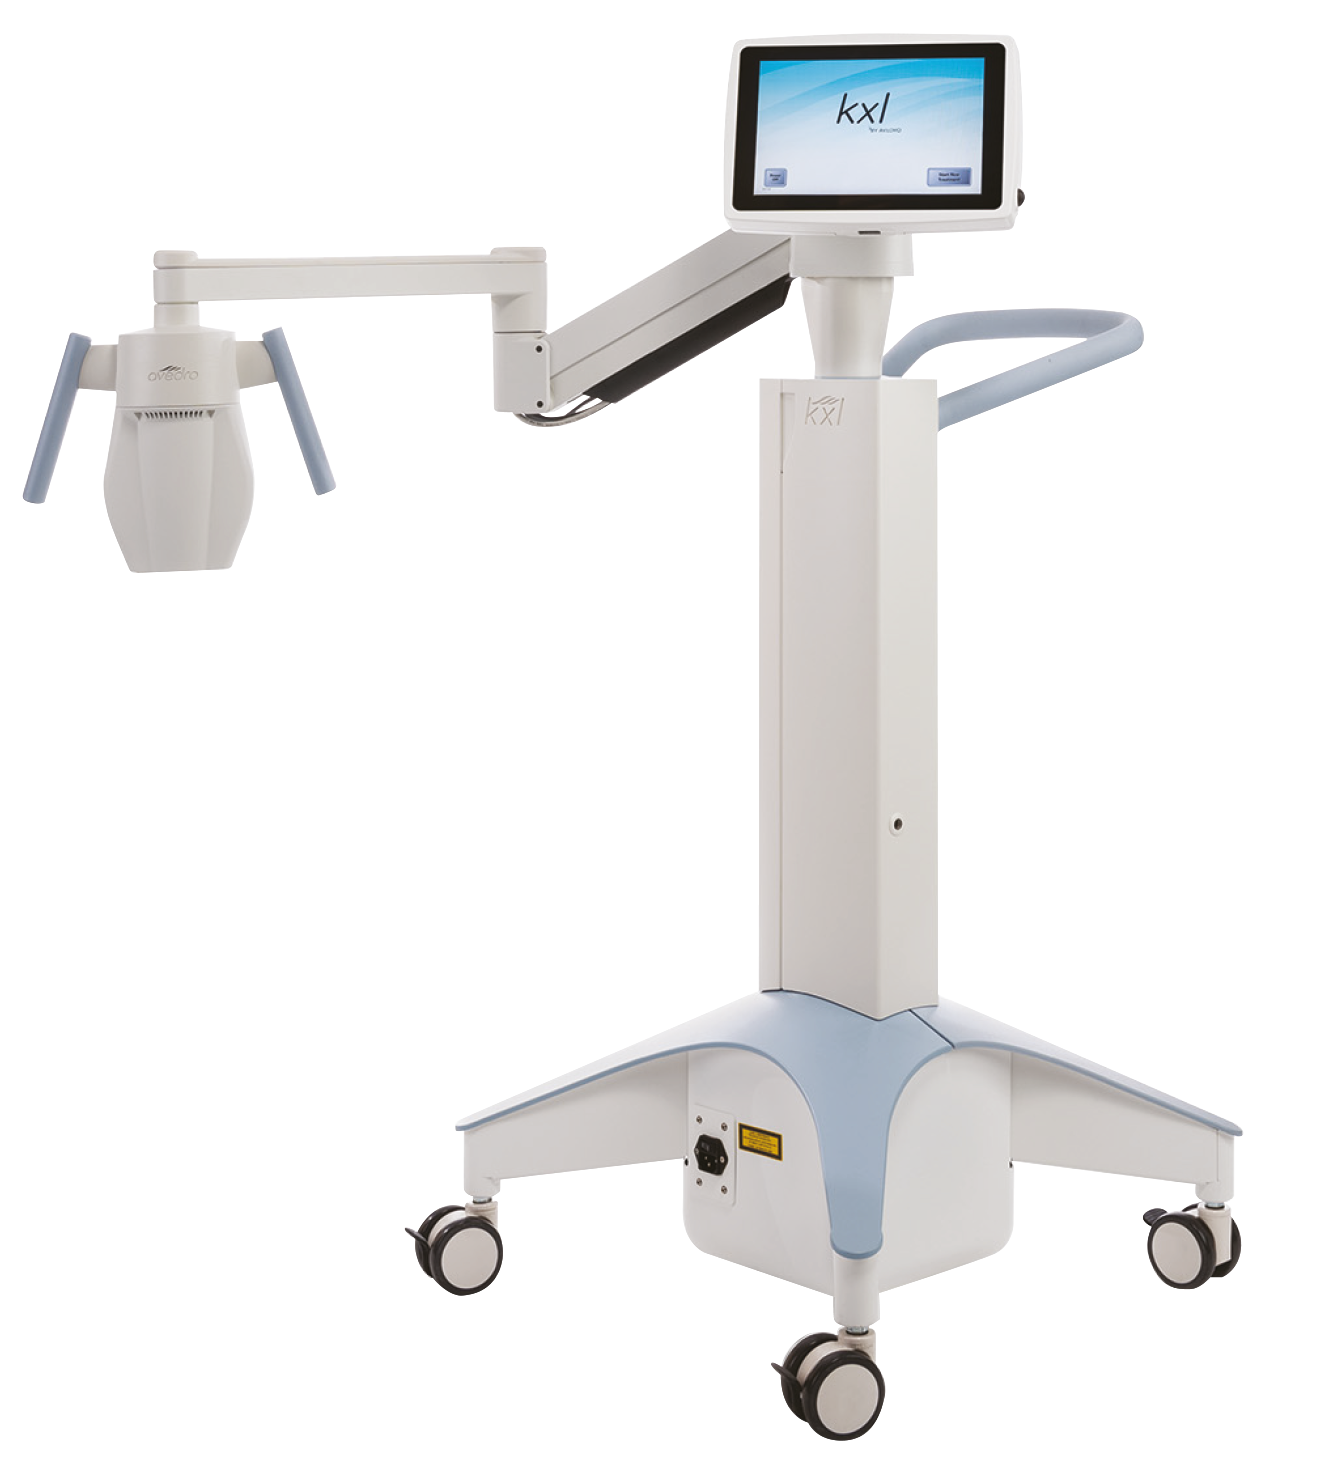
Corneal Cross-linking
Corneal cross-linking works by applying drops of riboflavin (vitamin B₂) to the cornea and then exposing it to ultraviolet-A (UVA) light. This triggers chemical reactions that create new “cross-links” between the collagen fibres in the cornea, strengthening its structure and making it more rigid. By reinforcing and stabilizing the cornea, CXL helps prevent further thinning and bulging — the hallmark of keratoconus — and thus halts or greatly slows the progression of the disease. Although CXL doesn’t reverse existing corneal shape changes or restore perfect vision, it often preserves current vision levels and reduces the risk that the patient will eventually need a corneal transplant.

KXL + PTK
Combining CXL with PTK leverages the strengths of both procedures: PTK uses an excimer-laser to gently smooth and regularize the surface of the cornea (epithelium removal with laser rather than mechanical scraping), which tends to reduce corneal irregularities and improve shape regularity before the cornea is stabilized. Then CXL strengthens the cornea by creating additional molecular cross-links in the collagen lamellae, stiffening the corneal structure and halting further thinning or bulging. The result is dual benefit: improved visual quality (less distortion and better visual acuity) and long-term biomechanical stability — meaning reduced risk of further progression of keratoconus. Many surgeons and studies consider CXL + PTK (or more broadly “CXL-plus” protocols) the best-available balance today between stabilizing the diseased cornea and rehabilitating vision, especially in patients whose corneas are thick enough and whose disease is moderate.

Dr. Sasan Niknam MD FRCS (C)
Dr. Niknam is the premier Corneal Specialist in Toronto Canada as well as Sheraz Iran. As a published author of studies regarding various corneal diseases including Keratoconus, Dr. Niknam is considered the preeminent authority on Corneal diseases and Keratoconus.